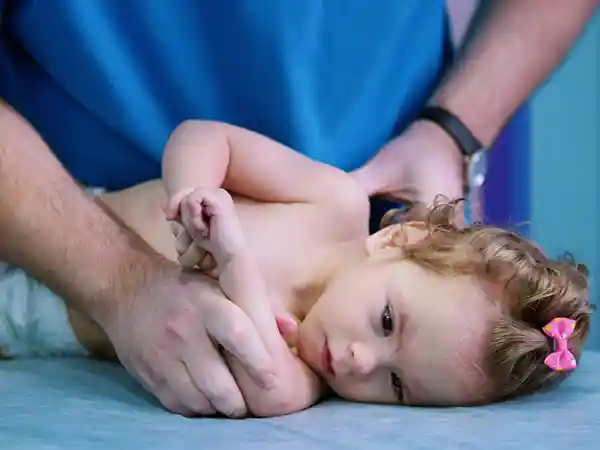
Erb’s palsy is a nerve injury that occurs when the brachial plexus (the bundle of nerves running from the neck to the shoulder) is stretched or torn during birth. Most children recover significantly with early treatment, but the cause is often a preventable mistake during delivery.
U.S. babies are born with Erb’s palsy each year, AAOS
3–6 months
When the full extent of nerve injury typically becomes clear
3× higher
Risk of brachial plexus injury when shoulder dystocia is present
What is Erb’s palsy?
Erb’s palsy (also known as Erb-Duchenne palsy or brachial plexus birth palsy) is a nerve injury that occurs when the delicate bundle of nerves running from the neck to the shoulder is stretched or torn during birth, leaving a newborn with muscle weakness or, in serious cases, complete paralysis of the affected arm.
The brachial plexus powers nearly every movement in the shoulder, arm, elbow, wrist, and hand. When it is compromised, the impact on a child’s mobility and development can be significant, especially without early intervention. Erb’s palsy is also a sign that something may have gone wrong during delivery, whether due to physical stress, poor fetal positioning, or a preventable medical error.
If a child shows signs of weakness, limited arm movement, or a noticeable difference in limb posture shortly after birth, further evaluation is essential. Identifying Erb’s palsy early allows children to begin a treatment plan that can dramatically improve their quality of life.
Erb’s palsy typically develops during complicated or high-risk deliveries. The injury occurs when an infant’s neck is forcefully stretched to one side, most often due to shoulder dystocia, when the baby’s shoulder becomes stuck behind the mother’s pelvic bone during birth. See our deeper guide on Erb’s palsy risk factors for a full breakdown of what increases risk.
In these tense moments, excessive pressure applied to guide the baby through the birth canal can overstretch or tear the upper brachial plexus nerves, usually at the C5–C6 vertebral levels. This trauma may result in anything from mild muscle weakness to more severe cases involving a limp arm and complete loss of sensation. Many cases are preventable. See prevention strategies for the obstetric protocols that reduce risk.
Whether the injury heals on its own or requires surgical intervention depends on the type and extent of nerve damage, which is why early and accurate diagnosis is critical.
Can you recover from Erb’s palsy?
According to the American Academy of Orthopaedic Surgeons (AAOS), most children with Erb’s palsy recover significant or full function in the affected limb, especially with early diagnosis, proper physical therapy, and in select cases, surgery. Timely medical care can make all the difference in long-term outcomes. See our guide on long-term effects for the lifespan view.
Recovery depends heavily on the type of nerve injury. Mild nerve stretching (neuropraxia) often resolves within three months with conservative therapy. More severe injuries such as ruptures and avulsions do not heal naturally and require surgical repair. The key is acting quickly: delaying treatment reduces the window for successful nerve regeneration and functional recovery. For families exploring promising treatment frontiers, see our latest research guide.
1 in 1,000
U.S. babies born with Erb’s palsy annually
3 months
When therapy can begin for mild cases
6–9 months
Surgery window for severe cases that don’t respond to therapy
Four types of brachial plexus injury
The type of Erb’s palsy depends on the extent of nerve damage within the brachial plexus. These are classified into four primary categories, each with different implications for recovery and treatment, from mild stretching to complete nerve avulsion.
Mildest
Neuropraxia, nerve stretching
The most common and least severe type. The nerve is stretched but not torn, often producing a burning or tingling sensation along the affected arm. Most infants with neuropraxia regain normal movement and feeling within about three months with conservative care like physical therapy, no surgery required.
Moderate
Neuroma, scar tissue forms
The nerve tears slightly and heals improperly, forming scar tissue that compresses the surrounding healthy nerves. This restricts nerve signals and causes partial muscle function loss. Children may recover some movement but often require targeted therapy (or surgery) to fully restore arm function.
Severe
Rupture, nerve completely torn
The brachial plexus nerve is completely torn, but not at the spinal root. Unlike neuropraxia or neuroma, ruptures do not heal on their own and require surgical intervention. Surgeons perform nerve grafting procedures to bridge the torn ends and restore some level of function to the arm and shoulder.
Most Severe
Avulsion, nerve torn from spinal cord
The most catastrophic type: the nerve is ripped away from the spinal cord entirely, causing permanent nerve damage. This can lead to complete paralysis, muscle atrophy, and in some cases affect the face and eyes. Surgery may offer some functional improvement by rerouting nearby nerves, but the damaged nerve itself cannot be reattached. Avulsions can also cause Horner’s syndrome: drooping eyelids, small pupils, and impaired eye movement.
Erb’s palsy vs. other types of palsy
Not all forms of “palsy” are the same. Understanding the difference is critical when navigating a diagnosis and evaluating legal options.
Erb’s palsy vs. cerebral palsy: Erb’s palsy is caused by physical trauma to the network of nerves in the neck and shoulder, not the brain. In contrast, cerebral palsy is the result of brain damage, often linked to oxygen deprivation or abnormal brain development before, during, or shortly after birth. They require very different treatment approaches.
Erb’s palsy vs. Klumpke’s palsy: Klumpke’s palsy is a much rarer brachial plexus injury. While Erb’s affects the upper nerves (C5–C6) and primarily impacts shoulder and upper arm movement, Klumpke’s involves the lower brachial plexus (C8–T1), causing weakness or paralysis in the hand and forearm muscles. Both interfere with voluntary movement but affect different regions.
Both Erb’s and Klumpke’s palsies are brachial plexus birth injuries and may be caused by excessive force during delivery. Both may support a birth injury lawsuit when medical negligence is involved.
How is Erb’s palsy treated?
Treatment depends on the severity of the nerve damage and how the condition progresses. Mild nerve injuries often respond well to therapy alone, while more severe cases require surgery. Acting early (within the first 6 to 9 months) significantly improves outcomes.
Physical therapy: the first line of care
Physical therapy typically begins as early as three weeks of age when symptoms persist beyond the newborn period. A licensed pediatric physical therapist uses gentle massage, passive and active range-of-motion exercises, and stretching techniques to improve flexibility, reduce stiffness, and build strength in the weakened arm. The goals are to prevent joint contractures, improve circulation, and encourage proper movement in the shoulder, elbow, and wrist. For many children with mild to moderate nerve damage, physical therapy alone can lead to significant functional recovery. Families also benefit from emotional support resources through the rehabilitation journey.
When a child’s grasping, holding, or reaching has not improved over the first four months, occupational therapy may be introduced. OT focuses on rebuilding the motor skills needed for independent everyday activity: muscle tone, fine motor control, and coordination. Through play-based tasks and structured exercises, therapists help children relearn how to use the affected arm and hand effectively, supporting everything from self-feeding to early developmental milestones.
Surgical options for severe cases
When nerve signals fail to return after 6 to 9 months, surgery may be necessary. Time is critical: early surgical intervention increases the chance of long-term recovery.
Nerve transfer surgery is the most common procedure. A healthy nerve from another part of the body is moved and connected to the injured brachial plexus. Over time, new nerve fibers grow into the affected area, reestablishing lost movement.
Tendon transfer surgery relocates a tendon from one muscle group to another, improving motion and stability in the shoulder, elbow, or wrist. These procedures are typically paired with post-operative therapy to maximize recovery.
Delaying therapy or surgery can reduce the likelihood of full recovery. The first few months of a baby’s life are a critical window for nerve healing. The sooner treatment begins, the better the outcome for your child’s mobility and strength.
How difficult deliveries lead to nerve injury
When complications arise during high-stress or prolonged labor, doctors must act quickly to avoid danger. But when excessive force is used or maneuvers are poorly executed, an infant’s neck and shoulder region may suffer serious nerve damage resulting in Erb’s palsy.
This most commonly occurs during complicated vaginal deliveries involving shoulder dystocia, a medical emergency where the baby’s shoulder becomes trapped behind the mother’s pelvic bone after the head has already emerged. When shoulder dystocia is present, the risk of brachial plexus injury increases nearly threefold.
Aside from shoulder dystocia, Erb’s palsy may also stem from fetal positioning or the baby’s size. An awkward position in the womb (such as breech or transverse lie) can increase tension on the brachial plexus during labor. A larger-than-average baby may have more difficulty passing through the birth canal, heightening the likelihood of shoulder entrapment and nerve injury. Doctors are expected to recognize and communicate these risks in advance.
Key risk factors for Erb’s palsy
Several conditions during delivery can significantly elevate the risk of brachial plexus injury. Doctors and hospital staff are trained to recognize and respond to these risk factors. When they fail to do so, it may constitute medical negligence.
Shoulder dystocia is the largest single risk factor and the one that demands trained maneuvers to resolve safely. Macrosomia, generally taken as a birth weight over 8.8 pounds, raises the likelihood of the shoulder catching. Forceps or a vacuum extractor can apply harmful lateral traction if misused. A second stage of labor running beyond an hour increases the load on the plexus. Forceful pulling on the arm or shoulder stretches or tears the nerves directly, which is the mechanism in most claims. An unfavorable pelvic shape narrows the margin. Force during an emergency cesarean extraction can produce the same injury. And a prenatal assessment that missed fetal size or positioning removes the chance to plan for any of it.
While not every case stems from error, many instances of Erb’s palsy are preventable and occur due to poor decision-making or excessive force by the delivering provider. When doctors or nurses fail to act according to accepted standards of care and that failure leads to injury, it may qualify as medical negligence.
Signs and symptoms of Erb’s palsy
Erb’s palsy symptoms often present early (sometimes right after birth), but the full injury may not become clear until a child is several months old. Symptoms primarily affect the shoulder, arm, and hand on one side of the body.
In the delivery room or nursery, the first signs are often visible to medical staff and parents. A newborn might show unusual arm posture or lack of movement on one side. Many children diagnosed with Erb’s palsy experience partial muscle weakness, while others face total paralysis of the affected arm.
If nerve function does not begin to return within the first 3 to 6 months, the damage may be more severe and long-term intervention may be necessary. Common symptoms to look for in the first 6 months include:
What parents notice is a mix of movement and sensation. Numbness or reduced feeling in the arm or hand. A weak grip, or difficulty holding anything. The arm hanging limply with the palm turned backward or inward. Restricted movement at the shoulder, elbow or wrist. Obvious weakness set against the other arm. And in the most severe cases, partial or complete paralysis of the limb.
Classic “waiter’s tip” position
One of the most recognizable signs of Erb’s palsy is the arm hanging straight down with the palm facing backward or inward, known as the “waiter’s tip” posture. If you notice this in your newborn, contact your pediatrician immediately.
Symptom checklist: could it be Erb’s palsy?
If your child is showing any of the following signs, consult a medical professional as soon as possible. Early diagnosis opens the door to the most effective treatment options.
The classic presentation is specific enough to recognize: the arm hangs straight down without bending at the elbow, and the palm faces backward or inward in what clinicians call the waiter’s tip position. A baby will not move that arm while crying, feeding or stretching. One arm looks weaker than the other and has less tone. Grip on the affected side is poor. Shoulder, elbow and wrist movement is limited, and sensation may be reduced. At the severe end the arm is partly or completely paralysed.
Don’t wait for a routine check-up if you suspect something is off. A doctor can assess your child’s condition and recommend early intervention. The first few months of a baby’s life are critical for nerve healing and developmental progress, catching Erb’s palsy early opens the door to the most effective treatments.
Erb’s palsy caused by medical mistakes
Unfortunately, many cases of brachial plexus nerve injury result from medical mistakes by doctors or hospital staff. When a child’s Erb’s palsy could have been avoided with safer delivery practices, families may have legal options, and the right to substantial compensation.
Medical negligence isn’t always obvious in the moment, but it can be identified through expert review of birth records, fetal monitoring logs, and provider decisions. Common errors that lead to Erb’s palsy include:
The failures that support a claim are narrow and documented. Excessive lateral traction on the head during a shoulder dystocia. Failure to recognize the dystocia or to run the recognized maneuvers in order. Improper use of a vacuum extractor or forceps. Failure to recommend a cesarean where macrosomia or pelvic factors indicated one. And an inadequate response to warning signs during labor, which the monitoring record documents minute by minute.
If a preventable mistake occurred, families may be entitled to compensation to help cover ongoing care, adaptive equipment, physical therapy, surgical costs, and long-term support. Our birth injury lawyers are available 24/7 to discuss your case at no cost, with no fee unless compensation is recovered.
Every state has a deadline for filing a claim. Review the statute of limitations for your state as early as possible to preserve your rights.
Free case review, no obligation
If you suspect medical mistakes played a role in your child’s Erb’s palsy, contact us today to speak with a lawyer or nurse about your options at no cost.
A weakness or paralysis of the arm caused by injury to the upper nerve roots of the brachial plexus, usually during delivery. The name refers to the specific pattern: the shoulder and elbow are affected while hand function is often preserved, producing the arm-down, palm-back posture called the waiter’s tip position.
Traction on the head and neck while the shoulder is impacted, which is why shoulder dystocia is the dominant risk factor. Macrosomia, a prolonged second stage, instrument-assisted delivery and unfavorable pelvic dimensions all raise the odds, and most of those are identifiable before labor begins.
Most recover. Across a referral series of 1,383 affected neonates, 72% to 74% resolved spontaneously, and at whole-population level, counting the milder cases that never reach a specialist, resolution ran to between 94.4% and 98.1%. Recovery is far more likely in the milder severity groups: 64% of Narakas I and II infants regained biceps function by three months against 9% of the Narakas III and IV group.
Therapy begins within weeks, with range-of-motion work to prevent contracture and splinting to hold position. Our page on physical therapy covers the underlying approach. Where biceps function has not returned by around three to six months, surgical referral becomes appropriate, and options include nerve grafting and nerve transfer. Timing is not flexible, because the window for reinnervating a muscle closes.
Clinically, by comparing the two arms. Someone else can move the affected arm through its range and the baby cannot, the Moro reflex is asymmetric, and the arm sits limp against the body with the forearm turned in. Testing supports that picture rather than replacing it, and a clavicle fracture has to be excluded because it produces an arm a baby will not move for mechanical reasons.
Watch for a stalled recovery rather than a slow one. Absent biceps function at three months is the marker that most changes the plan, since the evidence shows it separates the group that recovers spontaneously from the group that does not. Persistent asymmetry, contracture at the shoulder, or a limb that is not growing at the same rate all warrant reassessment.
Where the record shows a departure from the standard of care: excessive traction after impaction was recognized, dystocia maneuvers delayed or performed out of sequence, instruments misused, or a cesarean not offered where risk factors indicated one. Shoulder dystocia itself can occur without any error, so an honest review starts with the delivery record rather than the diagnosis.